EU Regulators Back Moving Teclistamab Earlier in Multiple Myeloma Treatment: What the MajesTEC-9 Data Actually Show
What this article covers
- Background: What Teclistamab Is and How It's Been Used So Far
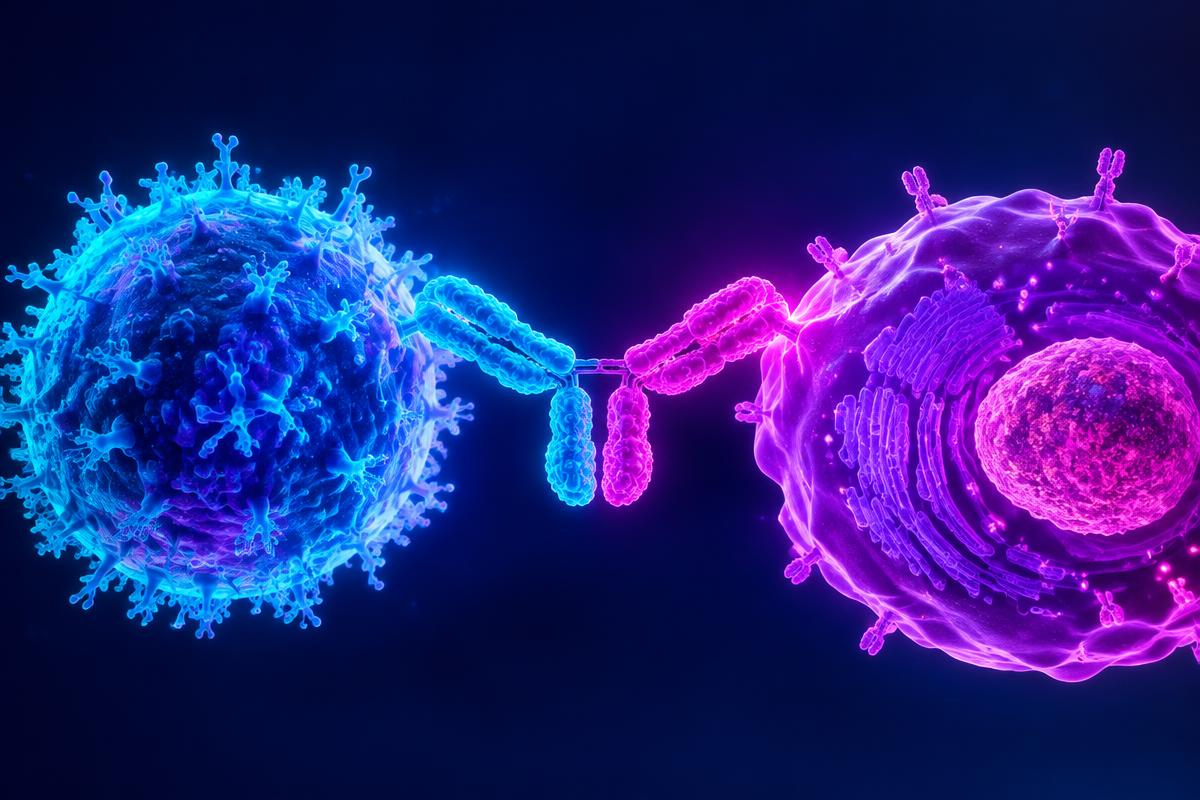
- Teclistamab is a "bispecific" antibody — a single molecule engineered to grab onto two different targets at once. One arm binds BCMA, a protein found on the surface of malignant plasma cells in multiple myeloma; the other arm binds CD3, a marker on the patient's own T-cells.
- What the CHMP Actually Recommended
- " The CHMP is the EMA's scientific advisory committee; its job is to review clinical data and issue an opinion, which is then sent to the European Commission for a legally binding marketing authorization decision. That final decision typically follows within roughly two months of a positive CHMP opinion, and it almost always follows the committee's recommendation — but as of this writing, teclistamab monotherapy in the one-prior-line setting is not yet an approved indication anywhere.
- The MajesTEC-9 Trial Behind the Recommendation
- The supporting data come from MajesTEC-9, a randomized Phase 3 trial that compared teclistamab monotherapy against physician's choice of two standard combination regimens — pomalidomide/bortezomib/dexamethasone (PVd) or carfilzomib/dexamethasone (Kd) — in patients with relapsed or refractory multiple myeloma who had received one to three prior lines of therapy. This was a difficult-to-treat population: roughly 85% of enrolled patients were already refractory to an anti-CD38 antibody and about 79% were refractory to lenalidomide, meaning most had already stopped responding to some of the field's most effective existing drugs.
- Important Caveats and Limitations
- The benefit came with a real, measurable safety cost that deserves equal weight. 5%.
- What This Means for Patients
- For now, nothing changes immediately for patients or prescribers: teclistamab's approved label, in both the EU and the US, still reflects its original later-line indications (plus the separate June 2026 combination-therapy expansion with daratumumab). Patients with relapsed multiple myeloma after just one prior treatment cannot yet obtain teclistamab monotherapy through routine, on-label prescribing based on this recommendation alone.
On September 18, 2026, the European Medicines Agency's Committee for Medicinal Products for Human Use (CHMP) issued a positive opinion recommending that teclistamab (TECVAYLI), Johnson & Johnson's bispecific T-cell-engaging antibody, be approved as a monotherapy for relapsed or refractory multiple myeloma after just one prior line of treatment — a major expansion from its current use as a later-line option for patients who have already exhausted several other therapies. The recommendation rests on Phase 3 data from the MajesTEC-9 trial showing a substantial reduction in the risk of disease progression or death compared with standard combination chemotherapy regimens. This article explains what a CHMP opinion actually is and isn't, what the underlying trial found, what real safety trade-offs came with that benefit, and what still has to happen before any patient's treatment changes.
Background: What Teclistamab Is and How It's Been Used So Far
Teclistamab is a "bispecific" antibody — a single molecule engineered to grab onto two different targets at once. One arm binds BCMA, a protein found on the surface of malignant plasma cells in multiple myeloma; the other arm binds CD3, a marker on the patient's own T-cells. By physically bridging the two, the drug forces T-cells into direct contact with myeloma cells and triggers an immune attack, without requiring the weeks-long manufacturing process that CAR-T cell therapies need. It's given as a subcutaneous injection rather than an infusion, which is part of what has made it attractive as a more accessible alternative to CAR-T in this disease.
Teclistamab has been available in the EU since 2022, but only for heavily pretreated patients — those who had already tried and failed at least three prior lines of therapy, including an immunomodulatory drug, a proteasome inhibitor, and an anti-CD38 antibody. Earlier this year, in June 2026, the CHMP separately recommended expanding teclistamab (in combination with daratumumab) into the second-line setting, based on a different trial, MajesTEC-3, which reported an 83% reduction in the risk of progression or death compared with standard-of-care combinations. September's opinion goes further still, addressing teclistamab used alone, after only a single prior treatment.
What the CHMP Actually Recommended
It's worth being precise about what happened this week, because "CHMP recommends" is often misread as "EU approves." The CHMP is the EMA's scientific advisory committee; its job is to review clinical data and issue an opinion, which is then sent to the European Commission for a legally binding marketing authorization decision. That final decision typically follows within roughly two months of a positive CHMP opinion, and it almost always follows the committee's recommendation — but as of this writing, teclistamab monotherapy in the one-prior-line setting is not yet an approved indication anywhere. It is a recommendation working its way through the European regulatory pipeline. Nothing has changed yet for a US patient: the FDA has not been reported to have taken any parallel action on this specific expanded use.
The MajesTEC-9 Trial Behind the Recommendation
The supporting data come from MajesTEC-9, a randomized Phase 3 trial that compared teclistamab monotherapy against physician's choice of two standard combination regimens — pomalidomide/bortezomib/dexamethasone (PVd) or carfilzomib/dexamethasone (Kd) — in patients with relapsed or refractory multiple myeloma who had received one to three prior lines of therapy. This was a difficult-to-treat population: roughly 85% of enrolled patients were already refractory to an anti-CD38 antibody and about 79% were refractory to lenalidomide, meaning most had already stopped responding to some of the field's most effective existing drugs.
On the trial's primary endpoint, progression-free survival, teclistamab reduced the risk of disease progression or death by 71% relative to the standard-of-care arm (hazard ratio 0.29, 95% CI 0.23–0.38, p<0.001). On the key secondary endpoint of overall survival, teclistamab reduced the risk of death by 40% (hazard ratio 0.60, 95% CI 0.43–0.83, p=0.002). The depth of response was also notably higher: 65.9% of teclistamab-treated patients achieved a complete response or better, versus 16.8% on standard therapy. Those are large, statistically robust effect sizes for a Phase 3 trial in this setting, and they are the reason regulators moved to recommend the drug for earlier use rather than reserving it for patients who have already run out of other options. These results were published in the New England Journal of Medicine.
Important Caveats and Limitations
The benefit came with a real, measurable safety cost that deserves equal weight. Overall adverse event rates were similar between arms (99.7% with teclistamab versus 97.9% with standard therapy), but higher-grade toxicity was more common with teclistamab: Grade 3 or 4 adverse events occurred in 84.9% of teclistamab patients versus 76.3% on standard therapy, and fatal (Grade 5) adverse events occurred in 6.5% versus 3.5%. Infections of Grade 3 or higher were also more frequent with teclistamab (41.6% versus 29.0%), although rates declined over the course of treatment. Teclistamab carries an existing boxed warning for cytokine release syndrome and neurologic toxicity, including immune effector cell–associated neurotoxicity syndrome, both known class effects of T-cell-engaging therapies that require monitoring, typically with inpatient step-up dosing when treatment begins. Median treatment duration was also longer on teclistamab (13.1 months versus 7.0 months), which is a marker of the drug's durability but also means more prolonged exposure to these risks. None of this negates the efficacy signal, but it means "earlier line" does not mean "lower risk," and the trade-off is one patients and physicians will need to weigh individually.
What This Means for Patients
For now, nothing changes immediately for patients or prescribers: teclistamab's approved label, in both the EU and the US, still reflects its original later-line indications (plus the separate June 2026 combination-therapy expansion with daratumumab). Patients with relapsed multiple myeloma after just one prior treatment cannot yet obtain teclistamab monotherapy through routine, on-label prescribing based on this recommendation alone. What has changed is the strength of the evidence base: a positive Phase 3 readout with a CHMP endorsement substantially raises the likelihood that this expanded use will become available to European patients within months, and increases the odds that a similar filing will eventually reach the FDA for review in the US.
What's Still Unknown, and What's Next
The European Commission's final decision on this specific recommendation has not yet been issued and does not have a confirmed date in the sources reviewed for this article. No FDA filing or review timeline for the equivalent US indication has been announced. Longer-term data on quality of life, and on how outcomes compare directly against newer CAR-T options increasingly used in earlier lines of myeloma treatment, will also matter for how oncologists ultimately sequence these therapies.
Bottom Line
This is genuine, well-documented positive news: a large, randomized Phase 3 trial showed that moving a T-cell-engaging bispecific antibody earlier in multiple myeloma treatment substantially reduced the risk of progression and death compared with standard combination chemotherapy, and European regulators have formally endorsed that shift based on the data. But a CHMP opinion is a recommendation, not a final approval, and the underlying trial also showed a real increase in high-grade toxicity and fatal adverse events relative to the comparator arm. Patients should understand this as a promising and likely-to-be-approved expansion in progress, not as a treatment already available for earlier-line use, and should discuss the specific risk-benefit trade-offs with their oncologist once (and if) the expanded indication is formally authorized.
Key Questions Answered
- Does a CHMP positive opinion mean teclistamab is approved for earlier use?
- No. The CHMP is the EMA's scientific advisory committee; its opinion goes to the European Commission, which issues the legally binding authorization, typically within about two months. As of now, teclistamab monotherapy after one prior line is not an approved indication anywhere.
- What did MajesTEC-9 find?
- Teclistamab reduced the risk of disease progression or death by 71% versus standard combination regimens (hazard ratio 0.29, 95% CI 0.23–0.38, p<0.001) and the risk of death by 40% (hazard ratio 0.60, 95% CI 0.43–0.83, p=0.002). Complete response or better was reached by 65.9% of teclistamab patients versus 16.8% on standard therapy.
- What are the safety trade-offs?
- Grade 3 or 4 adverse events occurred in 84.9% of teclistamab patients versus 76.3% on standard therapy, and fatal (Grade 5) events in 6.5% versus 3.5%. Grade 3 or higher infections were more frequent (41.6% versus 29.0%). Teclistamab also carries an existing boxed warning for cytokine release syndrome and neurologic toxicity.
- Does this change anything for US patients?
- No. The FDA has not been reported to have taken any parallel action on this specific expanded use, and teclistamab's US label still reflects its existing indications.
Sources
- CHMP recommends approval of Johnson & Johnson's TECVAYLI (teclistamab) in relapsed/refractory multiple myeloma after at least one prior therapy — GlobeNewswire / Johnson & Johnson press release, 2026 — https://www.globenewswire.com/news-release/2026/09/18/3364625/0/en/chmp-recommends-approval-of-johnson-johnson-s-tecvayli-teclistamab-in-relapsed-refractory-multiple-myeloma-after-at-least-one-prior-therapy.html
- Teclistamab Snags Positive CHMP Opinion for Relapsed/Refractory Multiple Myeloma — OncLive, 2026 — https://www.onclive.com/view/teclistamab-snags-positive-chmp-opinion-for-relapsed-refractory-multiple-myeloma
- Teclistamab in Multiple Myeloma with One to Three Previous Lines of Therapy (MajesTEC-9) — New England Journal of Medicine, 2026 — https://www.nejm.org/doi/abs/10.1056/NEJMoa2603870
- MajesTEC-9 Data Add to Accolades for Teclistamab in Multiple Myeloma — AJMC, 2026 — https://www.ajmc.com/view/majestec-9-data-add-to-accolades-for-teclistamab-in-multiple-myeloma
- CHMP recommendation advances Johnson & Johnson's TECVAYLI (teclistamab) plus daratumumab as a potential standard of care for relapsed/refractory multiple myeloma — Johnson & Johnson press release, June 2026 — https://www.jnj.com/media-center/press-releases/chmp-recommendation-advances-johnson-johnsons-tecvayli-teclistamab-plus-daratumumab-as-a-potential-standard-of-care-for-relapsed-refractory-multiple-myeloma
- U.S. FDA Approves TECVAYLI (teclistamab-cqyv), the First Bispecific T-cell Engager Antibody for the Treatment of Patients with Relapsed or Refractory Multiple Myeloma — Johnson & Johnson press release — https://www.jnj.com/media-center/press-releases/u-s-fda-approves-tecvayli-teclistamab-cqyv-the-first-bispecific-t-cell-engager-antibody-for-the-treatment-of-patients-with-relapsed-or-refractory-multiple-myeloma
Related Articles
- Clinical Applications
What Does the FDA's CAR-T Boxed Warning on Secondary Cancers Actually Show?
The FDA's 2024 class-wide boxed warning on secondary T-cell cancers after CAR-T flagged a real signal — but the largest datasets since show the absolute risk is low and CAR-T's benefits still outweigh it.
- Clinical Applications
Why Doesn't Immunotherapy Work Well for Pancreatic Cancer? What the Evidence Shows
Most pancreatic tumors are genetically quiet and walled off by dense stroma, so checkpoint inhibitors rarely work — except in the small MSI-H/dMMR subset. Personalized mRNA vaccines are the most promising lead.
- Clinical Applications
FDA Grants Breakthrough Therapy Designation to WU-CART-007 for Relapsed T-Cell Leukemia and Lymphoma: What the Phase 1 Data Show
An off-the-shelf CD7-targeted CAR-T produced a 91% response rate in evaluable Phase 1 patients — in cancers with no new FDA-approved therapy since 2005.